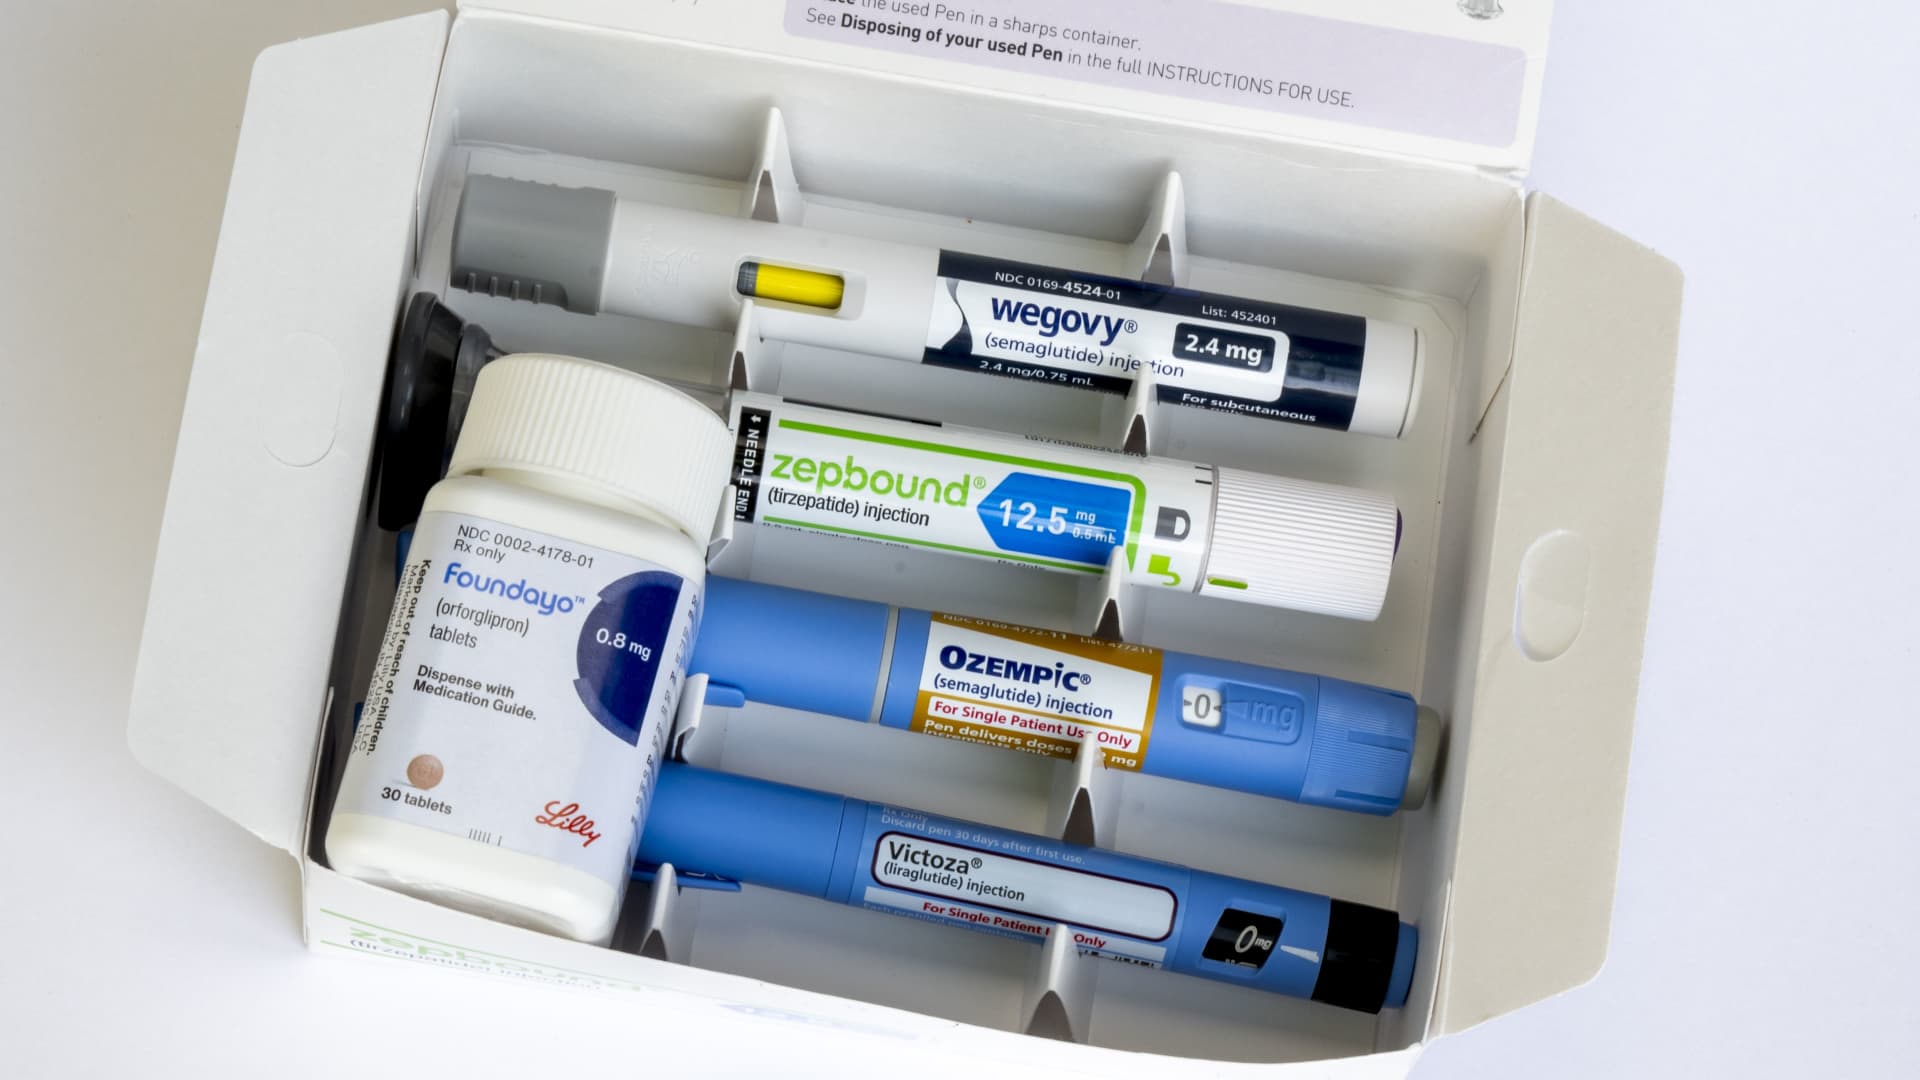
The next generation of blockbuster obesity drugs are not trying to replace GLP-1 drugs.
However, drug manufacturers are developing treatments that can complement existing drugs and improve weight loss, or offer new options to the millions of people who may not benefit from GLP-1.
This is the early potential of new combinations of injections, pills and regimens that target the amylin pathway, which includes hormones released in the pancreas along with insulin that help regulate hunger and satiety. Amylin gives Eli Lily, New and several other companies, other biological levers to treat obesity and Type 2 diabetes, as a stand-alone treatment or layered on top of existing drugs.
Lilly offered a glimpse of that strategy this week.
The company’s experimental amylin-targeting drug, eloralintide, helped produce more weight when combined with tirzepatide – the active ingredient in the blockbuster shots Zepbound and Mounjaro – in a Phase 2 trial for obese and Type 2 diabetic patients.
At 48 weeks, those who received the highest-dose combination lost an average of 23.3% of their body weight, compared with 14.8% among those who took only the high-dose tirzepatide. These figures are based on an efficacy analysis that assumes patients remain on treatment in the trial.
“These are encouraging results,” said Benjamin Bikman, a professor at Brigham Young University and a leading expert on metabolic health and insulin resistance. “Adults with type 2 diabetes typically lose less weight on these therapies than those without diabetes.”
Lilly developed eloralintide as a stand-alone treatment and as part of these combo therapies. These two components create what some analysts see as a key future franchise for the company.
Leerink Partners analyst David Risinger forecasts $23.2 billion in annual sales for Lilly’s eloralintide product by the end of 2035. He said he expects the standalone drug to launch first in 2029, followed by the combo in 2030.
“There are millions of individuals, potentially more than 10 million people, who have tried GLP-1 and failed because of efficacy reasons, tolerability issues, or genetic issues that just didn’t respond,” Risinger told CNBC. “We think this novel mechanism, this amylin analog … will provide a new treatment alternative for patients, both as a monotherapy and as a combination therapy.”
Risinger said he sees greater potential for standalone eloralintide because of the “large standalone patient pool” that hasn’t had success on existing GLP-1s. Lilly still sees a clear opportunity to pair the drug.
“Patients may not be getting what they need from a drug like tirzepatide,” Ken Custer, president of Lilly Cardiometabolic Health, said in an interview. “They may not be getting what they need from a drug like eloralintide on its own.”
Bikman also said he sees the combo as an opportunity for patients who started on tirzepatide alone but saw a plateau in weight loss.
But Lilly still has a lot to prove. The data comes from a relatively small Phase 2 study that the company must confirm in Phase 3 trials, which are expected to begin this year.
Lilly also aims to improve how well patients tolerate the combo regimen in future studies. More patients taking two drugs – 10.8% to 27%, depending on the dose – stopped treatment due to side effects, compared to 2.9% of people on tirzepatide alone in the trial.
“Therapies are only effective if the patient can sustain them, so tolerability in Phase 3 will be as important as efficacy,” Bikman said.
Dr. Caroline Apovian, co-director of the Center for Weight Management and Wellness at Brigham and Women’s Hospital, added that “27% is not a good number.”
However, these results add to the growing body of evidence that amylin may be an important tool in the fight against obesity and diabetes.
Lilly isn’t the only one betting that amylin could be a building block for the next generation of obesity drugs. Novo has been pursuing a similar strategy for years.
Novo’s experimental amylin-based drug, cagrilintide, has shown beneficial weight loss as a stand-alone treatment in late-stage trials. Combining it with semaglutide – together dubbed CagriSema – has produced greater weight loss in clinical studies. CagriSema is expected to be launched early next year, followed by standalone cagrilintide and a higher-end version of CagriSema in 2028.
Novo is also developing another treatment called amycretin, or zenagamtide, which is a single molecule that will target GLP-1 and amylin to treat obesity and Type 2 diabetes. The Danish drugmaker tested it as a once-a-week injection and a daily oral tablet, and the drug showed promising Phase 2 results earlier this year.
Some companies, including Pfizer, AstraZeneca and Viking Therapeuticsalso developed its own amylin product.
The first – and so far only – amylin therapy was approved in the US more than two decades ago as an additional injection for people with diabetes who use insulin. But adoption is limited in part because it requires multiple injections a day.
New therapies in development are long-acting, meaning they are designed to mimic hormones in a sustained way and can be taken once a week, Bikman said.
Amylin helps signal satiety, suppresses appetite and slows the movement of food through the stomach, similar to what GLP-1 does. But amylin achieves this by acting on a completely different biological pathway.
“It’s the same result, but a different approach,” Bikman told CNBC.
The idea is that targeting multiple pathways can produce more weight loss or other metabolic benefits than a single pathway can achieve on its own, and without relying on higher drug doses.
New data from Novo this week suggests that the benefits may go beyond physical changes.
CagriSema reduced “eating disorder” – constant thoughts about food – and showed improvements for organ and bone health in a one-year functional magnetic resonance imaging study, which is a noninvasive way to measure brain activity during specific tasks. Novo said CagriSema changes the way the brain responds to tempting, high-calorie foods in areas linked to cravings, pleasure and self-control in obese or overweight people.
“The signals in the brain change in a way that is associated with a better quality of life,” said Martin Holst Lange, Novo’s chief scientific officer, in an interview.
Developing treatments that target multiple hormone pathways rather than one is part of a broader shift in the obesity drug race, even beyond amylin.
Tirzepatide has paired GLP-1 with GIP, while Lilly’s experimental drug retratrutide also adds glucagon to the mix. Retatrutide has produced some of the largest weight loss results reported in obesity drug trials to date, and Bikman says published data on the drug show reductions in liver fat, triglycerides and fasting insulin.
It is too early to definitively say whether the combination of amylin drugs can be superior to tirzepatide or next generation treatments. They must clear clinical trials and regulatory review first.
But all of the drugs being developed work toward a broader goal shared by some drug makers: giving patients a variety of obesity and diabetes treatment options to meet their individual needs.